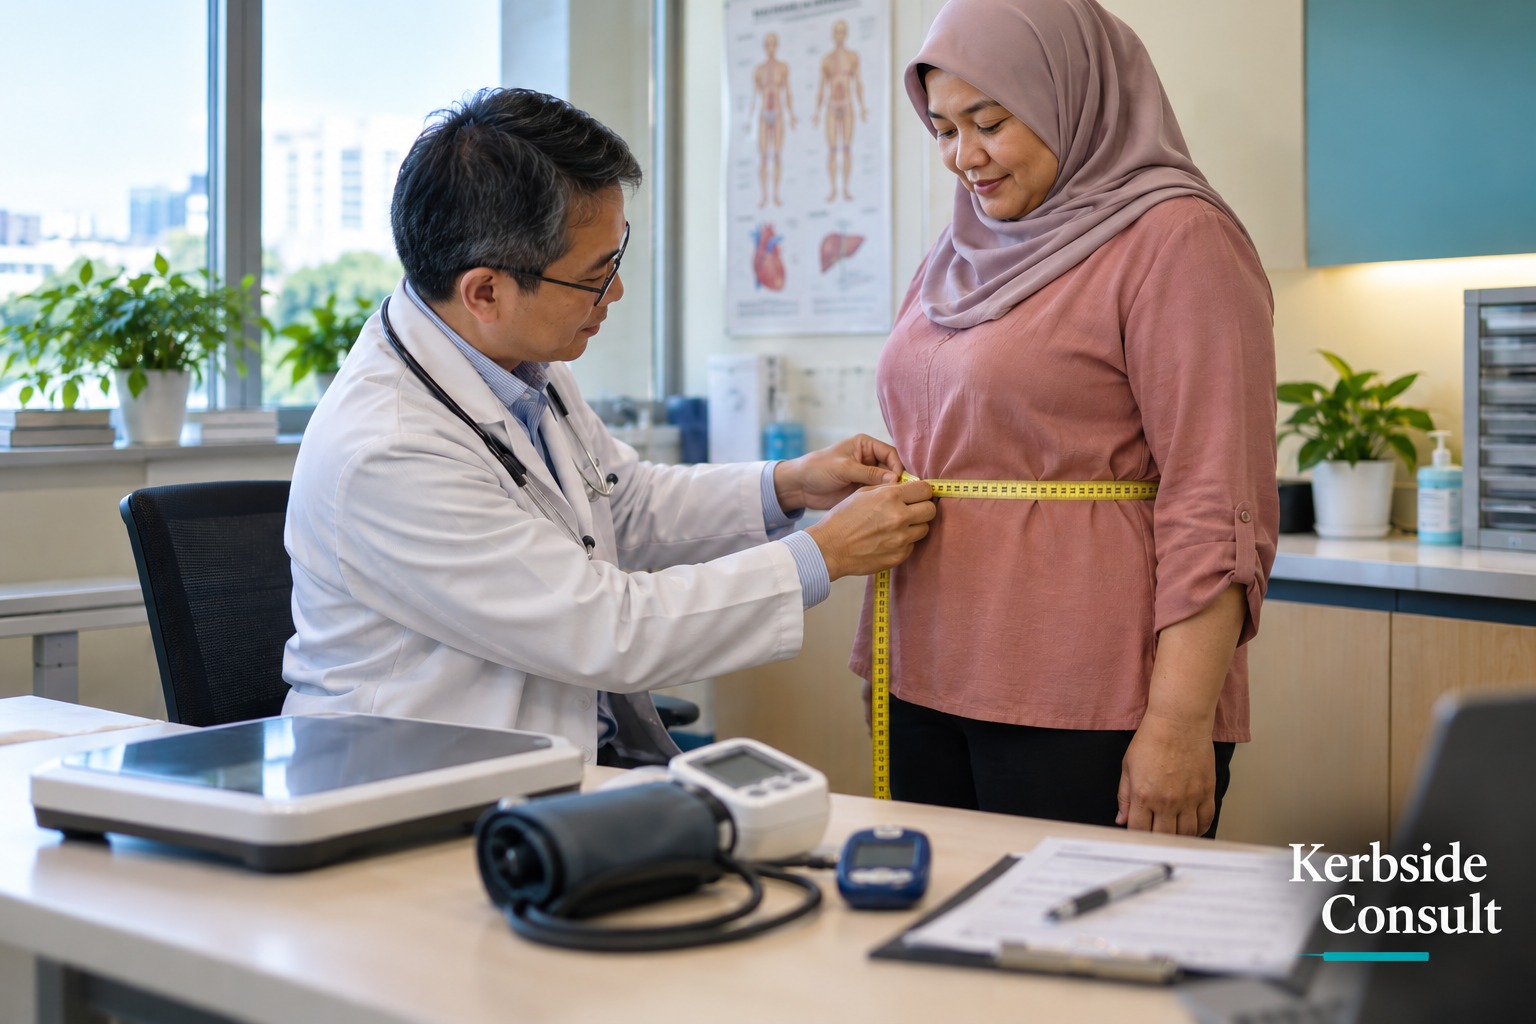
A glucose result can take over a consultation. It gives us a number to explain, a target to discuss, perhaps a treatment to change. But what about the waist, the blood pressure, the lipids? About one in six Malaysian adults has diabetes, and more than a third meet criteria for metabolic syndrome (NHMS 2023). Those are different measures of a substantial burden. My argument is simple: give the tape measure a place beside the scale, then look at and manage the whole patient. [1]
1. One in six, often undiagnosed
Malaysia's National Health and Morbidity Survey (NHMS) put diabetes prevalence among adults at 15.6% in 2023, down from 18.3% in 2019 (NHMS 2023 methodology paper, Scientific Reports). Roughly two in five adults with diabetes were unaware they had it. Among adults aged 18–29 with diabetes, that rises to 84% unaware (NHMS 2023: Key Findings, Institute for Public Health). [1][2]
This is familiar ground from my own research. In the Screening India’s Twin Epidemic (SITE) study, which I co-authored, 15,662 outpatients were recruited across eight Indian states in 2009–2010. Diabetes was identified in 34.7%; among participants without a previous diagnosis, 7.2% were newly diagnosed and 18.4% had prediabetes. The study’s clinic population limits how far we can take those figures. Newly diagnosed cases were fewer than known cases, but screening still found people whose diabetes had gone unrecognised (Joshi, Saboo, Vadivale et al., 2012). [3]
2. Beyond the glucose result
Finding diabetes is one part of the work. Looking at the risks around it is another, and Malaysia’s figures give us reason to keep looking. Estimated diabetes prevalence fell between 2019 and 2023, while obesity continued to rise. The two surveys used different glucose meters, and the 2023 report does not state fasting status or cut-offs, so that comparison needs care. It is tempting to supply a tidy explanation involving food, activity and an ageing population. These surveys cannot tell us how much each contributed. [1][2][4]
NHMS put overweight-or-obesity (BMI ≥25 kg/m²) at 54.4% of adults in 2023 — up from 44.5% in 2011, climbing at every survey point between (47.7% in 2015, 50.1% in 2019). Abdominal obesity also increased, from 45.4% in 2011 to 54.5% in 2023 (NHMS 2023: Key Findings). [1]
3. What the tape adds to the scale
The scale gives us weight. Add height and we can calculate BMI. The tape brings abdominal size into the conversation. Both measurements have limits: neither directly measures visceral fat, and neither diagnoses diabetes. Their usefulness lies in what we do next with the blood pressure, glucose and lipid results.
Why measure the waist at all? Asian populations, including Malays, tend to carry more body fat than Caucasians at the same BMI, by about 3 to 5 percentage points in one review. [5] A WHO expert consultation found that many have a high risk of type 2 diabetes and cardiovascular disease at BMIs below the international overweight cut-off of 25 kg/m². It proposed public-health action points at 23 and 27.5 kg/m², which is why the Asian definitions of overweight and obesity are lower. [6] An increased waist points to more abdominal fat, particularly visceral fat, for which the tape is a simple proxy. This is the metabolically unhealthy fat. It is an independent marker of metabolic and cardiovascular risk, and it is linked to insulin resistance, higher glucose, abnormal lipids and cardiovascular events such as heart attacks and strokes. A person with a modest BMI can therefore still carry substantial risk, which is why the tape belongs beside the scale. [7]
There is already a place for the tape measure in Malaysian clinical practice. The 2023 Malaysian obesity guideline recommends annual BMI screening for adults, with waist circumference providing additional information about abdominal adiposity and cardiometabolic risk. The Quick Reference Guide recommends yearly BMI and waist measurements, although the full guideline recognises limitations to waist circumference, particularly at BMI above 35 kg/m². The guideline uses the lower Asian BMI cut-offs of 23 kg/m² for pre-obesity and 27.5 kg/m² for obesity, whereas NHMS’s combined overweight-and-obesity figure uses BMI ≥25 kg/m². These definitions serve different purposes, and changing the definition changes who is counted. For the waist, the guideline defines abdominal obesity as 90 cm or more in men and 80 cm or more in women, measured midway between the lowest rib and the iliac crest. It describes waist as most useful at normal or overweight BMI, and unnecessary above 35 kg/m². [8][1]
Population data add a caveat for men. Cheong and colleagues analysed 32,703 adults in NHMS 2006. Depending on whether diabetes, hypertension or hypercholesterolaemia was the target, optimal waist cut-offs ranged from 81.4–85.5 cm in men and 79.8–80.7 cm in women, and they proposed 81 cm and 80 cm respectively (Cheong et al., 2014). The women’s figure is close to the guideline’s 80 cm. For men, 81 cm is well below 90 cm, so some men with risk factors may fall under the guideline threshold. A lower cut-off also flags more people who do not have those risk factors, and a research-derived cut-off is not automatically a clinical recommendation. These are 2006 data and do not replace the guideline cut-offs. [9]
The local evidence also asks us to be measured in our enthusiasm. In a separate population-based study of 2,572 adults aged 25–64, using 2005/2006 surveillance data, waist did not significantly outperform BMI in either sex when identifying two or more of the blood-pressure, glucose and lipid abnormalities associated with metabolic syndrome. The researchers deliberately left waist out of that definition, so the tape was not being judged against itself. Performance varied by age, sex and ethnicity (Cheong et al., 2015). That is enough reason for me to use both measurements, and to resist declaring a universal winner. [10]
A newer option is the waist-to-height ratio. NICE’s 2025 obesity guideline advises measuring it alongside BMI in adults with a BMI below 35 kg/m², treating 0.5 to 0.59 as increased risk and 0.6 or above as further increased risk, and advising people to keep their waist under half their height. Pooled analyses suggest it tracks diabetes more closely than BMI, though studies differ considerably. I have not found Malaysian data testing it against diabetes, and the Malaysian guideline still uses the sex-specific waist cut-offs above. It is easy to explain to a patient, but it is not yet a Malaysian cut-off. [11][12][8]
4. The company diabetes keeps
NHMS 2023 estimated that 35.9% of Malaysian adults — approximately 8.5 million people — met criteria for metabolic syndrome. Abdominal obesity was present in 83% of that group (NHMS 2023 Key Findings; Malaysian national analysis, 2025). There is a catch in interpreting that 83%: abdominal obesity is itself one of the criteria used to identify the syndrome. The figure describes the cluster; it cannot establish that waist is its earliest warning. These data also do not tell us how many people knew they had the syndrome. [1][13]
The same need to look beyond glucose continues after diagnosis. A study of 288,913 people with type 2 diabetes in Malaysian public primary care found, at baseline, 84.5% overweight or obesity, 78.5% abdominal obesity, 81.6% hypertension and 76.1% dyslipidaemia. Its overweight-or-obesity definition used BMI ≥23 kg/m², so the 84.5% cannot be compared directly with NHMS’s BMI ≥25 figure. Mean HbA1c was approximately 8%, and 40.9% had HbA1c below 7% (Wan et al., 2023). Those figures describe people already receiving care in that setting. For the consultation, the implication is straightforward: the glucose result deserves attention, and so do the blood pressure and lipids. [14]
5. What it costs to miss it
Among medically certified deaths in Malaysia in 2024, diabetes ranked third, accounting for 5.2%, behind ischaemic heart disease and pneumonia. But that is only the part of the national record with medically certified causes: 67.3% of all deaths. The missing third matters when we describe what Malaysians die from (DOSM, Statistics on Causes of Death, Malaysia, 2025). [15]
In a West Malaysian cohort of people with diagnosed type 2 diabetes aged 40–79, the 2019 standardised mortality ratios were 1.83 in men and 1.85 in women compared with the general population. The comparison covers deaths from all causes; it cannot attribute that excess entirely to diabetes. Overall mortality rates were unchanged across 2010–2019, with increases in some subgroups. The study could not tell us the causes of death (Lim et al., 2023). [16]
Malaysia has been working on that gap. A 2014–2016 verbal-autopsy study of nearly 15,000 deaths in 19 districts reassigned some poorly classified deaths to diabetes, but its figures describe that selected group and are not a national diabetes mortality rate (Rao et al., 2019). [17]
Then there is the bill. A joint Ministry of Health–WHO report estimated direct health-care costs of diabetes at RM4.38 billion in 2017, compared with RM3.93 billion for cardiovascular disease and RM1.34 billion for cancer. The date belongs beside the number: this is a historical costing exercise, not today’s annual bill (MOH–WHO original costing report, 2022). [18]
6. Earlier diagnosis
What should happen in the consultation? Malaysia’s 2020 diabetes guideline recommends annual screening using fasting plasma glucose or HbA1c for people with risk factors and those aged 30 or older (full CPG, screening recommendations, p. 30). Measure the waist, ask about family history, and arrange the appropriate blood tests. A tape measurement cannot confirm diabetes. For someone without symptoms, the guideline requires two abnormal results, either appropriate tests from the same sample or repeat testing. [19]
7. Better control
Once diabetes is diagnosed, a reading needs a plan. What is the patient meant to do with the number, and when should they ask for help? NHMS 2023 reported that only about two in five adults with known diabetes owned a glucometer (NHMS 2023 Key Findings). A 2026 Malaysian study of 396 adults attending five primary-care clinics found that 59.3% reported currently self-monitoring blood glucose. That was a convenience sample, and “currently monitoring” could mean testing at any frequency. We cannot turn it into a claim about regular testing (Ong et al., Malaysian Family Physician, 2026). [1][20]
Continuous glucose monitoring (CGM) belongs in this treatment conversation too, and the evidence for people not using insulin is growing. The US CONNECT randomised trial of 283 adults with type 2 diabetes not using insulin (HbA1c ≥7.5%, 21 primary-care practices) reported, in a conference presentation, a 0.9-percentage-point greater HbA1c reduction with CGM than routine care over 26 weeks. Three of its authors are Dexcom employees, several others report Dexcom research support, and I could not find a full peer-reviewed results paper. Guidance is moving, but unevenly. Malaysia’s 2020 guideline formally recommends considering CGM only for patients on intensive insulin therapy. The ADA’s 2025 Standards first advised considering CGM in adults with type 2 diabetes on glucose-lowering agents other than insulin (grade B). Its 2026 edition recommends CGM for people on non-insulin therapies that can cause hypoglycaemia (grade C) and on any treatment where it helps management (grade E). How well the findings translate to Malaysian practice needs its own assessment. [21][22][19][23][24]
- Give the tape a place beside the scale. The Malaysian obesity Quick Reference Guide recommends yearly BMI and waist measurement; the full guideline qualifies the use of waist circumference. Measure consistently, write it down, and use the next visit to discuss what has changed. [8]
- Look at the company glucose keeps. Check blood pressure and lipids as well. A reassuring weight or waist should not cancel other important screening that is due because of age or the presence of other risk factors that commonly accompany diabetes.
- Make the glucose monitoring plan simple, usable and relevant. Agree which readings to take, what they mean and when to seek help. Ask about the cost of strips and supplies. Owning the glucose meter is only the beginning.
- For the patient: bring the readings you have and ask which checks are due. You do not need to arrive with every answer. A useful question is: “We have checked my sugar and blood pressure. What else needs checking?”
The waist measures something important: the amount of fat in the abdomen, which is linked to a higher risk of heart and kidney complications. [7][25] My advice is simple: measure the waist, keep the scale, and follow through on the blood pressure, lipids and glucose. Give the whole patient a consultation.
Acknowledgment
I am grateful to Dr Chan Siew Pheng, Emeritus Professor (Endocrine Medicine) and Consultant Endocrinologist, MBBS (Mal), FRCP (Edinburgh), AM (Mal), for her review of this piece and her critical feedback. The judgements and any errors remain mine.
Sources worth your time
- 1. Institute for Public Health. National Health and Morbidity Survey (NHMS) 2023: Non-Communicable Diseases and Healthcare Demand—Key Findings [Internet]. Shah Alam: Ministry of Health Malaysia; 2024 [cited 2026 Oct 13]. Available from: https://repository.nih.gov.my/entities/publication/a5d57850-9773-46ef-8c70-6eb30ab0b831
- 2. Institute for Public Health investigators. Conducting the National Health and Morbidity Survey 2023 in Malaysia with focus on methodology and main findings on non-communicable diseases. Sci Rep. 2025;15:25531. doi:10.1038/s41598-025-08311-9. Available from: https://www.nature.com/articles/s41598-025-08311-9
- 3. Joshi SR, Saboo B, Vadivale M, et al. Prevalence of diagnosed and undiagnosed diabetes and hypertension in India—results from the Screening India’s Twin Epidemic (SITE) study. Diabetes Technol Ther. 2012;14(1). doi:10.1089/dia.2011.0243. Available from: https://doi.org/10.1089/dia.2011.0243
- 4. Ismail H, Rodzlan Hasani WS, Saminthan TA, Mat Rifin H, Ab Majid NL, Ahmad A, et al. Prevalence of diabetes and its associated factors among the Malaysian adults population: National Health and Morbidity Survey 2019 [conference poster P-04]. Institute for Public Health, Ministry of Health Malaysia; 2020 [cited 2026 Oct 13]. NMRR-18-3085-44207(IIR). Available from: https://zenodo.org/records/4011326
- 5. Deurenberg P, Deurenberg-Yap M, Guricci S. Asians are different from Caucasians and from each other in their body mass index/body fat per cent relationship. Obes Rev. 2002;3(3):141-146. doi:10.1046/j.1467-789x.2002.00065.x. Available from: https://doi.org/10.1046/j.1467-789x.2002.00065.x
- 6. WHO Expert Consultation. Appropriate body-mass index for Asian populations and its implications for policy and intervention strategies. Lancet. 2004;363(9403):157-163. doi:10.1016/S0140-6736(03)15268-3. Available from: https://doi.org/10.1016/S0140-6736(03)15268-3
- 7. Neeland IJ, Ross R, Després JP, et al. Visceral and ectopic fat, atherosclerosis, and cardiometabolic disease: a position statement. Lancet Diabetes Endocrinol. 2019;7(9):715-725. doi:10.1016/S2213-8587(19)30084-1. Available from: https://doi.org/10.1016/S2213-8587(19)30084-1
- 8. Ministry of Health Malaysia. Clinical practice guidelines: management of obesity. 2nd ed. [Internet]. Malaysia: Ministry of Health Malaysia; 2023 [cited 2026 Oct 13]. Available from: https://mems.my/cpg-management-of-obesity/
- 9. Cheong KC, Ghazali SM, Hock LK, et al. Optimal waist circumference cut-off values for predicting cardiovascular risk factors in a multi-ethnic Malaysian population. Obes Res Clin Pract. 2014;8(2):e154-e162. doi:10.1016/j.orcp.2013.03.004. Available from: https://pubmed.ncbi.nlm.nih.gov/24743011/
- 10. Cheong KC, Ghazali SM, Hock LK, et al. The discriminative ability of waist circumference, body mass index and waist-to-hip ratio in identifying metabolic syndrome: variations by age, sex and race. Diabetes Metab Syndr. 2015;9(2):74-78. doi:10.1016/j.dsx.2015.02.006. Available from: https://pubmed.ncbi.nlm.nih.gov/25819369/
- 11. National Institute for Health and Care Excellence. Overweight and obesity management (NICE guideline NG246): identifying and assessing overweight, obesity and central adiposity [Internet]. London: NICE; 2025 Jan 14 [updated 2026 Jan 8; cited 2026 Oct 13]. Available from: https://www.nice.org.uk/guidance/NG246/chapter/identifying-and-assessing-overweight-obesity-and-central-adiposity
- 12. Savva SC, Lamnisos D, Kafatos AG. Predicting cardiometabolic risk: waist-to-height ratio or BMI. A meta-analysis. Diabetes Metab Syndr Obes. 2013;6:403-419. doi:10.2147/DMSO.S34220. Available from: https://doi.org/10.2147/DMSO.S34220
- 13. Wan KS, Mohd Yusoff MF, Mat Rifin H, et al. The prevalence of metabolic syndrome and the associated factors in a multiethnic upper-middle-income country in Asia: findings from a nationwide community-based study in 2023. BMC Public Health. 2025;25:1482. doi:10.1186/s12889-025-22762-9. Available from: https://link.springer.com/article/10.1186/s12889-025-22762-9
- 14. Wan KS, Mustapha F, Chandran A, et al. Baseline treatments and metabolic control of 288,913 type 2 diabetes patients in a 10-year retrospective cohort in Malaysia. Sci Rep. 2023;13:17338. doi:10.1038/s41598-023-44564-y. Available from: https://www.nature.com/articles/s41598-023-44564-y
- 15. Department of Statistics Malaysia. Statistics on Causes of Death, Malaysia, 2025 [Internet]. Putrajaya: Department of Statistics Malaysia; 2025 [cited 2026 Oct 13]. Available from: https://www.dosm.gov.my/uploads/release-content/file_20260316130724.pdf
- 16. Lim LL, Abdul Aziz A, Dakin H, Buckell J, Woon YL, Roope L, et al. Trends in all-cause mortality among adults with diagnosed type 2 diabetes in West Malaysia: 2010–2019. Diabetes Res Clin Pract. 2023;205:110944. doi:10.1016/j.diabres.2023.110944. Available from: https://pmc.ncbi.nlm.nih.gov/articles/PMC10701628/
- 17. Rao C, Omar MA, Ganapathy SS, Tamin NSI, et al. Strengthening mortality statistics for health programs in Malaysia: lessons from the field. Dr Sulaiman Al Habib Med J. 2019. doi:10.2991/dsahmj.k.191214.003. Available from: https://doi.org/10.2991/dsahmj.k.191214.003
- 18. Ministry of Health Malaysia, World Health Organization. The direct health-care cost of noncommunicable diseases in Malaysia [Internet]. Malaysia: Ministry of Health Malaysia; 2022 [cited 2026 Oct 13]. Available from: https://www.moh.gov.my/moh/resources/Penerbitan/Rujukan/NCD/NCD_Laporan/HEALTH-COST_of_NCDs-7-WEB.pdf
- 19. Ministry of Health Malaysia. Clinical practice guidelines: management of type 2 diabetes mellitus. 6th ed. [Internet]. Putrajaya: Ministry of Health Malaysia; 2020 [cited 2026 Oct 13]. Available from: https://www.moh.gov.my/images/04-penerbitan/penerbitan-klinikal/panduan-amalan-klinikal/CPG_T2DM_6th_Edition_2020_13042021.pdf
- 20. Ong MEH, Yong XG, Mahalinggam K, Tan YL, Ismail NA, Yusof MR, et al. Prevalence, predictors, barriers and facilitators of self-monitoring of blood glucose in patients with type 2 diabetes: a multicentre cross-sectional study. Malays Fam Physician. 2026;21:30. doi:10.51866/oa.1058. Available from: https://pmc.ncbi.nlm.nih.gov/articles/PMC13242596/
- 21. American Diabetes Association. 82% of adults with type 2 diabetes not on insulin improve blood glucose levels [Internet]. ADA newsroom; 2026 [cited 2026 Oct 13]. Conference press release reporting the 26-week result; not a peer-reviewed full report. Available from: https://diabetes.org/newsroom/press-releases/82-adults-type-2-diabetes-not-insulin-improve-blood-glucose-levels
- 22. Oser T, Beck RW, Martens T, et al. 1170-OR: CGM for adults with type 2 diabetes not on insulin therapy: the CONNECT randomized controlled trial. Diabetes. 2026;75(Suppl 1):1170-OR. Conference abstract describing design and baseline characteristics; results are not included. doi:10.2337/db26-1170-OR. Available from: https://doi.org/10.2337/db26-1170-OR
- 23. American Diabetes Association Professional Practice Committee. 7. Diabetes technology: Standards of Care in Diabetes-2025. Diabetes Care. 2025;48(Suppl 1):S146-S166. doi:10.2337/dc25-S007. Available from: https://doi.org/10.2337/dc25-S007
- 24. American Diabetes Association Professional Practice Committee. 7. Diabetes technology: Standards of Care in Diabetes-2026. Diabetes Care. 2026;49(Suppl 1):S150-S165. doi:10.2337/dc26-S007. Available from: https://doi.org/10.2337/dc26-S007
- 25. Japar KV, Hariyanto TI, Mardjopranoto MS. Relationship between phenotype models based on waist circumference and triglyceride levels and the risk of chronic kidney disease: a systematic review and meta-analysis. J Obes Metab Syndr. 2023;32(3):236-246. doi:10.7570/jomes23037. Available from: https://doi.org/10.7570/jomes23037